
Background:
The World Health Organisation recently urged for cost-effective solutions for NCDs (Non-Communicable Disorders) and mental health amidst slowing progress for their management strategies. There are huge burdens of disabilities due to chronic ailments and a suffering person loses many productive years of life due to pain /disability, , . Pain management by nonpharmacological noninvasive therapies like Rakken-ho therapy (RHT) is also possible and well published, yet majorly for musculoskeletal low back pains. Effect of maneuvers of this alturistic Yoga promoting well-being is inspired by Budhist tradition from India adopted in Japan. RHT using foot and hand manuover is propagated in Japan by Yugen Yamanaouchi -connected to Buddhist principles – Shingon Buddhist priest in Japan. It has been part of health management not only its origin in India but across the globe. There is evidence of about 525 types of nonpharmacological non-invasive therapeutic modalities, in clinical practice worldwide. RHT is one among those modalities and is recently regaining popularity as mainstream therapeutics for various ailments to maintain wellbeing,. With increasing skilled human resources / trained therapists and patients benefitting from this therapy, its documentation and validation are a felt need, hence its quantitative assessment recorded in Indian circumstances in this report.
About the Rakkenho: Rakkenho is a Japanese word which means- Joy of life – this maneuver /technique for wellbeing is traditionally authentically and widely practiced among the Japanese population, so there it is considered more as life style practice termed as ayurvedic massage rather a therapeutic modality. Yugen Yamanauchi’s center in Japan is teaching Rakkenho to students coming from outside Japan. Japanese learn it by traditional family practice or by attending traditional temple retreats in areas like Nara- Japan. Documenting/proving effectiveness may not have been felt due to its traditional nature. Research study is not generally done on age old time tested traditional practices, especially if they are there for a long time and have proven benefits/become a part of life. It is like brushing teeth on a daily basis, so research has not been done to document its benefits. However, during 2020, when Sri Sri Ravishankar ji, Art of Living found this tradition on his visit to Japan, he considered it useful to revive in India too for wellbeing, hence started its training in India. Though Japanese learn it by family tradition, but for outside Japan students a few training centers are there in Japan under supervision of Shingon Buddhist Institution. Sri Sri initiated sending Indian students there to revive this lost wealth of useful therapy for health and wellbeing and his master trainers trained in Japan started training and giving therapy in India16, ,.
Currently understanding of mechanism of action are majorly based on the way therapy imparted by focus of intervention on major lymphatic drainage areas- lymphatic nodes of groin and axilla and by observed benefits in circulatory system problems, i.e. varicose vein, conditions affected by lymphatic and blood circulation- feedback expressed for perceived benefits from recipients. There is tremendous scope of further research specially a lymphoscintigraphy scan- a nuclear medicine imaging test that maps how fluid flows through lymphatic system pre and post RHT. It is essential to explore mechanism of action as there is a dearth of published scientific literature currently. Further research on the mechanism will not only open the plethora of its mechanism /reason for its benefits but also create awareness of this non invasive non pharmacological way to manage pain and suffering.
Though exact mechanism need further research however it is already known that Lymphatic system of body plays a crucial role in maintaining flow of fluids in body and play important role for removing body toxins/ waste and unwanted material from body tissues, a vital role in the body immunity, fluid balance. Lymphatic channels collect excess fluid from tissues and return it to blood stream and prevent toxic collections and promote wellbeing. It is through lymphatic vessels of intestine where lacteals absorb dietary fats and fat soluble vitamins from digestive track and transport to blood stream. Metabolic waste is channled through lymphatic system. Unlike arterial flow, flow of lymph is not controlled by heart. It is controlled by movement of body, muscle contractions, physical activities, massage, and deep breathing excersizes which propel lymph.
RHT maneuver works on body zones (major lymphatic plexes /nodes of groin and axilla) where major lymphatice nodes are placed (Figure 1 shows the major action points for manuover during RHT) and enhances the lymphatic circulation in body tissues by use of rhythmic strokes and its specialized pressure movements around major lymph node areas to stimulate the lymphatic flow. Various symptoms of lymphedema (lymphatic swelling due to lymphatic fluid buildup), lymphadenopathy (enlarged lymph nodes), various circulatory disorders, varicose veins etc. are observed affected by RHT hence provide clue on its mechanism of action.
Figure1: Image showing major lymphatic nodes ares of human body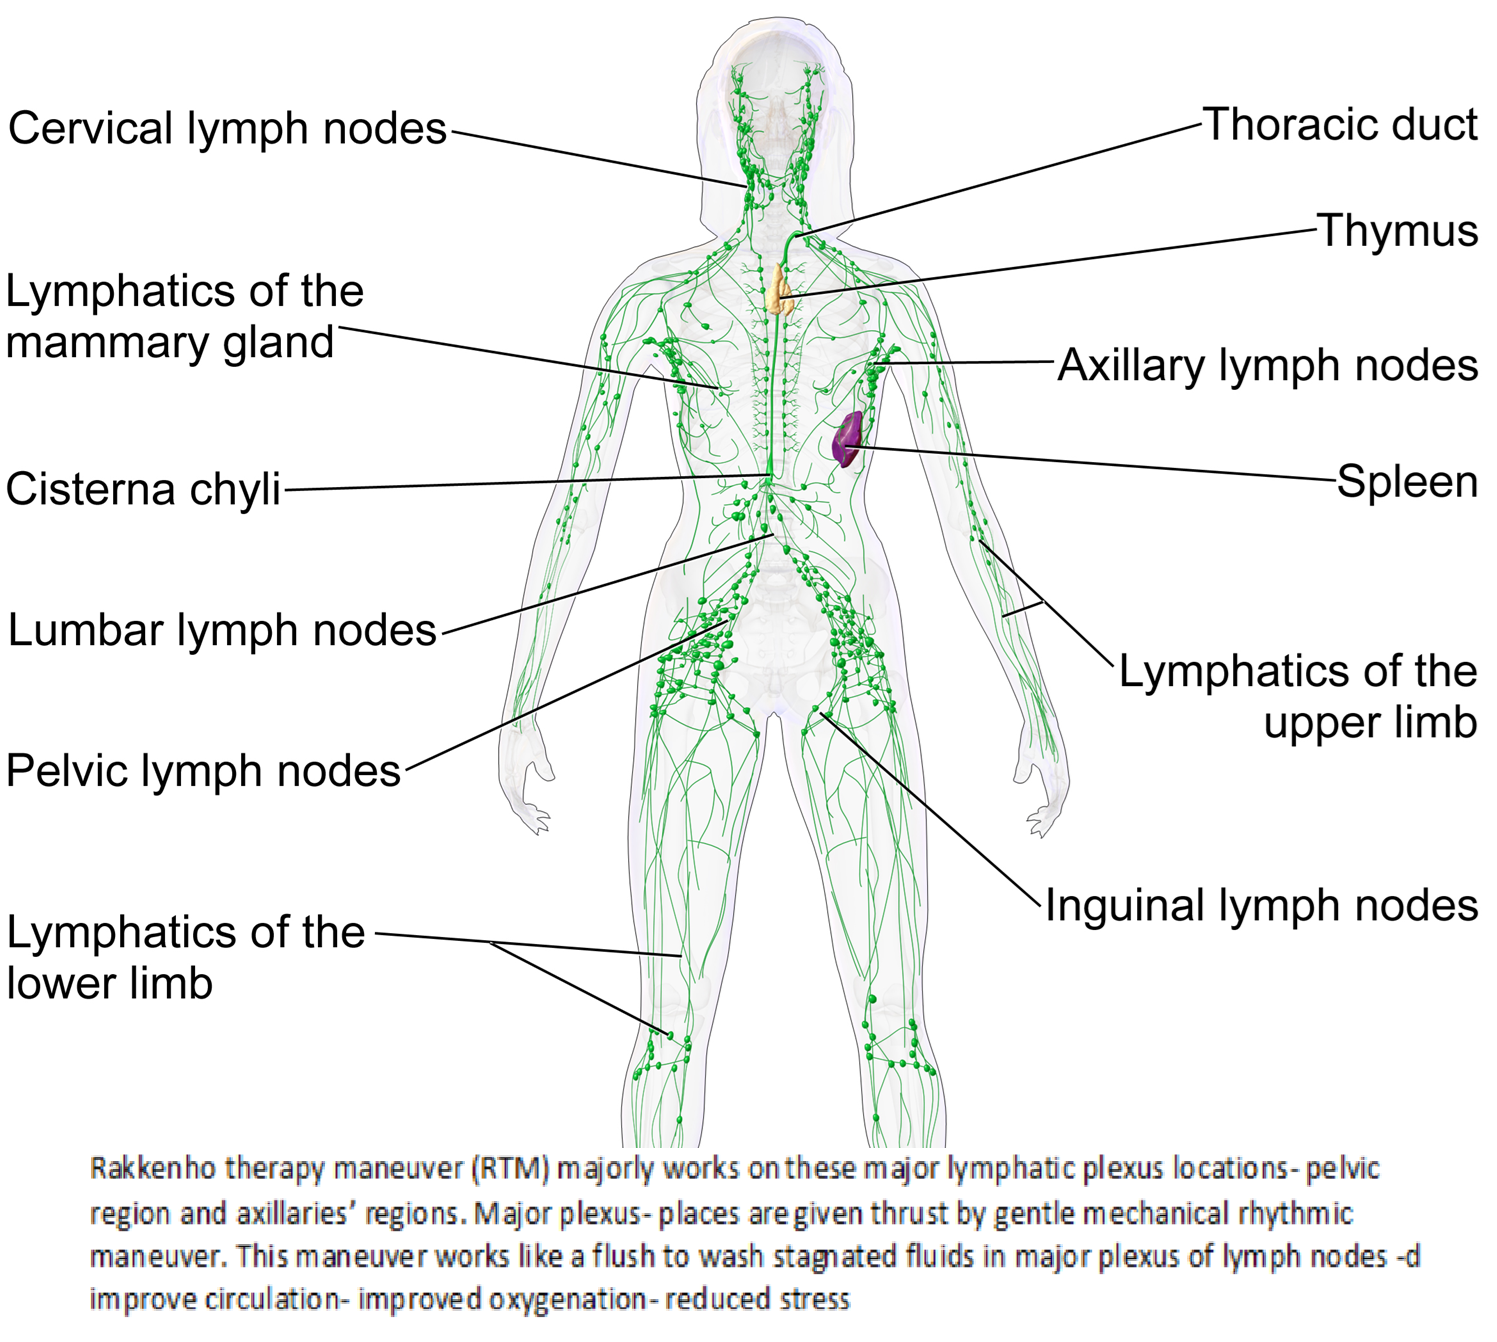
Methods to impart intervention: Preparation (The receiver lies fully clothed on a mat, while the giver uses balance. Initial Pressure (Kakushin): The giver faces away and presses down with both heels on the receiver’s soles (Kakushin points), moving rhythmically, Shoulder & Arm Work (Gokumu): The giver uses their foot to press down on the receiver’s axillary lymphatic plexus area around shoulder (Gokumu point) and along the arm to the fingertips, moving from shoulder to hand. Spinal Work: The giver sits astride the receiver’s knees, brings palms together (palms facing down), and slowly presses down the length of the backbone. Energy & Mantra Work– The session often ends with palms together in a prayer-like pose, sometimes chanting an enlightenment mantra to promote holistic balance17.
Study methods:
In this observational study, strobe guidelines (22 point’s checklist) are followed for reporting perceived experience of recipients of RHT. After informed consent, one online in depth questionnaire was filled by the first 31 receivers of Rakkenho therapy. Inclusion criteria was middle aged self consenting persons who were having some chronic morbidities- not responding to ongoing management. Though an exclusion criterion is certainly there for Rakkenho treatment, those who have undergone any type of surgery in past 6 months are not entitled to get therapy. Known case of kidney or gall stone, hernia, severe mental or physical disabilities are excluded to avoid unforeseen situation, however none of study participant had any condition making them liable for exclusion. By chance all consenting adults in our pilot study were having none of the conditions rendering them excluded for therapy hence no stringent exclusion was applicable for receivers of therapy. It was being done to get pilot testing data to get subjective as well as objective experience from the reciepients. Incidently middle aged both gender with chronic health conditions and middle socioeconomical status, highly lietrate turned out as consenting recipients. Purpose was to observe effectiveness, tolerability in diverse health conditions of adults. All the recipients consented for filling feedback form so none was exluded for absecence of consent. Study location was Art of Living center in South Extention New Delhi. No randomization of participants was done; all the reciepinets of therapy during April 2024-25 filled the questionnaire of feedback/ experience as all were lieterate, filled online by them using their android enabled phones. All received 45 minutes RHT session once a day for 3 to 5 consecutive days at their convenient time of the day irrespective of empty or full stomach. Their pre and post RHT feedbacks from google forms were downloaded in excel sheet and analysed in SPSS version 19 by April 2025. The questionnaire was bilingual- Hindi and English for easy understaning of the north Indian participants. Coding of downloaded data and statistical analysis using SPSS version 19 to derive p-value test of significance was done at Indian Council of Medical Research, New Delhi.
The scale of 1 to 10 was used to report pain, sleep quality, joint movements as was used in studies using Numeric rating scale,. For pain Zero is considered no pain; 1 to 3 is mild pain; 4 to 6 is moderate pain and 7 to 10 is severe pain. For sleep 0 to 3 highly disturbed /no sleep in night, 4 to 6 is mild to moderate disturbed sleep and 7 to 10 is sound /good leep.
Painless more pain
1 -2- 3- 4- 5- 6- 7- 8- 9 -10
Sleep (poor quality) sleeps good quality
1 -2 – 3 – 4 – 5 – 6 – 7 – 8 – 9 -10
Joint movement Joint movement better
1 -2 – 3 – 4 – 5 – 6 – 7 – 8 – 9 -10
Body flexibility Low Good body flexibility
1 -2 – 3 – 4 – 5 – 6 – 7 – 8 – 9 -10
Results:
Demographical and morbidity profile of 31 study participants receiving 3 to 5 sessions of Rakkhenho is given in Table 1.
| Gender | n | % |
| Male | 4 | 12.9 |
| Female | 27 | 87.1 |
| Total | 31 | 100.0 |
| Education | ||
| Doctor | 9 | 29.0 |
| Engineer | 2 | 6.5 |
| Post graduate | 14 | 45.2 |
| Undergraduate | 6 | 19.4 |
| Total | 31 | |
| Occupation | ||
| Business | 12 | 38.7 |
| Medical related/Doctor | 11 | 35.5 |
| Housewife | 2 | 6.5 |
| Govt. job | 3 | 9.7 |
| Teacher | 3 | 9.7 |
| Total | 31 | 100.0 |
| What motivated you to take rakkenho session | ||
| Self decision after listening word by mouth | 14 | 45.2 |
| On recommendation of family/ friend | 12 | 38.7 |
| On recommendation of a Doctor | 5 | 16.1 |
| Having any morbidity | 22 | 70.4 |
| No morbidity | 9 | 29 |
| Back pain | 1 | 3.2 |
| BP raised, stress | 2 | 6.5 |
| Diminished vision | 1 | 3.2 |
| Fibroid breast | 1 | 3.2 |
| Gastritis/indigestion | 3 | 9.7 |
| Hypothyroidism, Raised Blood Sugar, Over Weight | 3 | 9.7 |
| Lethargy weakness/ Over thinking | 2 | 6.5 |
| Met with an accident year ago and having pain in my leg after that | 1 | 3.2 |
| Pain stiffness after cancer treatment for mouth cancer | 1 | 3.2 |
| Pain stiffness all over body, knee joint | 5 | 16.2 |
| PCOD (polycysytic ovarian syndrome) | 1 | 3.2 |
| Uterine Fibroids & Ovarian Haemorrhagic cyst with hemarrogaic bleeding metroragea | 1 | 3.2 |
| Total | 31 | 100 |
Table 1 shows that all participants were middle aged middle income group and were highly educated, literate employed in intellectual professions. 29% wanted to explore therapy despite no serious medical problem, 71% had various ailments of back pain (3.2%) high blood pressure and stress (6.5%) diminished vision (3.2%), indigestion (9.7%) sugar/ thyroid/ endocrine/hormone related (19.3%) pain stiffness in joints (22.6%). Those who reported ailments considered it debilitating hampering their quality of life and making them unable to perform routine tasks. The duration of ailments was not documented but all had chronic history of more than 3 months and tried various therapeutic modilities and medicines as management for wellbeing.
| Study variable | Mean± SD | Std. Error | 95% Confidence Interval | Sig. (2-tailed) P value |
| Pain scored pre-therapy | 7.39±2.40 | 0.33 | 1.6-2.9 | 0.00 |
| Pain scored Post- therapy | 2.22±1.67 | 0.08 | 0.7-2.2 | |
| flexibility scored in body movements pre- therapy | 2.65±1.84 | 0.35 | 1.0-2.4 | 0.00 |
| flexibility scored in body movements post- therapy | 7.83±1.80 | 0.22 | 1.2-2.1 | |
| Sleep quality scores pre-therapy | 3.70±2.22 | 0.270 | 1.5-2.6 | 0.00 |
| Sleep quality scores post-therapy | 8.09±1.99 | 0.26 | 1.3-2.3 | |
| Scored joint movement quality pre-therapy | 3.43±2.10 | .266 | 1.4-2.5 | 0.00 |
| Scored joint movement quality post-therapy | 7.96+1.91 | -.065 | 1.2-2.4 |
Bootstrapping is a statistical procedure that resamples a single dataset to create many simulated samples. This process allows calculating standard errors, construct confidence intervals, and perform hypothesis testing for numerous types of statistics. Bootstrap methods are alternative approaches to traditional hypothesis testing and are notable for being easier to understand and valid for more than one conditions analysis.
| Bootstrap for Paired Samples Test | |||||||
| Mean | Bootstrapa | ||||||
| Bias | Std. Error | Sig. (2-tailed) | 95% Confidence Interval | ||||
| Lower | Upper | ||||||
| Pair 1 | pain in body | 5.174 | .002 | .518 | .001 | 4.175 | 6.217 |
| Pair 2 | flexibility in body movements | 5.174 | .012 | .475 | .001 | 4.262 | 6.130 |
| Pair 3 | sleep quality | 4.391 | .013 | .516 | .001 | 3.392 | 5.478 |
| Pair 4 | joint movement quality | 4.522 | .015 | .523 | .001 | 3.478 | 5.522 |
All four parameters of pain, sleep, joint comfort and flexibility showed significant difference on scales being rated pre and pot therapy and beneficial effect shown is significant (p value<0.05).
Figure 1 showing pain on 1 to 10 scales. Lagarithmic trendline showing higher pains pretherapy
Figure 2 shows the reported sleep quality improving on 1 to 10 scale
Figure 3 is showing body flexibility improving post therapy on 1 to 10 scales
Figure 4 shows post therapy higher score on 1 to 10 scales for joint movement levels
| 1 | Felt benefits described in own words by the reciepients |
| 2 | Feeling fresh and healthy |
| 3 | Better Flexibility, Less Lethargy |
| 4 | Body is so light and relax and no fatigue in body |
| 5 | Feeling Calm & peaceful |
| 6 | Clarity of mind,sharp mind, confidence, calmness of mind,physical fitness, healthy gut, stress gone, emotionally stable and strong, not panic, no need to take medicine |
| 7 | Energetic,no pain after therepy, |
| 8 | Feel more active |
| 9 | Feeling really relaxed |
| 10 | Feeling relaxed |
| 11 | Feeling well, light, sleeping well, vision improved |
| 12 | Good sleep rested calm and it is just like full body refreshing |
| 13 | High Energy and relaxation |
| 14 | high energy, able to do task more enthusiastically |
| 15 | i am sleeping and feeling of fear is gone, pain in knee has reduced, body feels light |
| 16 | i was completely out of focus and in great trauma/ depression pain in body |
| 17 | i was not able to focus on work due to pain and stiffness in nech, left arm was having tingling and pain, after 2 session symptoms gone completely |
| 18 | i was not able to sleep, now i am sleeping without pain, i remain happy without reason, feeling light, no fear of cancer, digestion is better |
| 19 | I was unbale to move body due to pain- and could go to toilet by self after first session, able to climb ladders now after 4 sessions. |
| 20 | It improves sleep and relaxes the body |
| 21 | Less pain, more flexibility |
| 22 | Lightness, energy of body and mind, relaxation, less beans et cetera |
| 23 | Mental health improved , Body pain gone, Stamina increased, sleep quality increased, Felt more happy lately |
| 24 | Mentally strong, no body pain, happiness, zero frustration |
| 25 | Mind is more settled, pain at body level has vanished |
| 26 | No tumore/ grouwth is felt in breast after 2nd session of rakkenho it was gone. |
| 27 | Painless Mensuration, Cool mind and calmness in overall behaviour |
| 28 | Sleep quality and leg pain gone, Everything was very interesting and good and I felt happy being a part of it |
| 29 | Tenderness & Heaviness in Breast before mensuration was absent this time. Mensuration was painless |
| 30 | The problems that existed in body and were unnoticed were also addressed through this, Earlier I had to wake up 3-4 times at night for urination…now after Rakkenho, I get up only in morning, Relaxed n calm mind, meditation is deeper than before. |
| 31 | Very refreshing, Earlier I used to feel lathargic and sleepy most of the time, but after session I felt relax and active |
| Experts from messages sent to authors on whatsapp “I feel blessed to attend these sessions as being hugely benefitted. I was having gastritis from year but severe from 3 months, affecting my other body systems as well like I was having palpitations, fast heart beat, then started having high BP and then got panic about my health. Then worsen the situation more, Being myself doctor, I got a lots of tests done, and was on allopathic medicine, and also ayurvedic medicine started after nadi pariksha, but after first two sessions, I reduced my medicine drastically because I did not feel the need. And by the end , I am absolutely fine. Not only physically but mentally also I feel relaxed, happy and confident now.” “I am feeling lighter, energetic and relaxed mentally, physically and emotionally.” “I feel so light and relax” “In my third therapy I had severe headache after 4th session it disappeared completely” “it is blessing to get it- it is highly recharging and rejuvenating” “It was a relaxing experience and got lot of relief” “It was very relaxing and rejuvenating” “It’s so wonderful therapy. My body pain gone. I am sleeping well. Flexability increased. mind cheerful” “My experience has been amazing. I have been relieved of body pain. Also better deep sleep. Who did this therapy is very passionate and dedicated towards this and motivated me to try it out, after first session itself, i looked forward for the next session. I could sleep better and get up in the morning in time. i could exercise better and could climb stairs easily which was difficut earlier” “Observed lots of Benefits on the mind side, I could see mind more calm and relaxed. Lots of old memories got cleared. Resulting in better clarity and focus. Also I got into action more and less procrastination” “Quality of life increases,self centred, physical, mental, emotional betterment” “Rakkenho therapy is good, it helps all irrespective of whether having any health or any kind of issue physical or mental.This is very good” “Very good experience I want to go daily but due to other commitments not able to go regularly. I feel good, relaxed mentally and physically. |
|
The response from reciepients has made it worth reporting. All participants expressed benefits, feeling better from therapy and none reported any side effect of any type- hence quantitative and qualutitative data of this pilot level observation study is quite encouraging to move for further studies in a randomised manner with long duration of follow-ups in disease specific conditions to find out for how much time the effect of such sessions remain there.
Discussion:
Integration of traditional nonpharmacological medical practices is increasing for wellbeing to lower the cost of care and to void complications of invasive intervention and medication is increasing hence role of RHT is about to increase. RakkenHo (RH) therapy a Japanese full-body therapy uses the soles of the feet and hands to apply gentle pressure to various pressure points and meridians throughout the entire body. Figure-1 shows major emphasis point during the therapy coincide to location of major lymph node plexux of body. It stimulates major lymphatic plexux node points in a specific sequence to promote the flow of fluid and energy (known as ki). RHT, a non pharmacological noninvasive mechanical manuover on lymphatic system affects body fluids circulation which in turn affects body temperature, distribution of nutrients and oxygen more effective. Reduction in pain, improved sleep, and general wellness reported in our study may possibly be by improved body fluid circulation, reduced tension and inflammation. By gentle rhythmic pressures on specific areas, RHT affects the movement of lymphatic fluid through the lymphatic vessels, and may be aiding in the removal of toxins, waste products, and stagnant fluids from the body and that may be possible mechamnism behind beneficial experience reported by receipients. Though, subjective feedbacks confirm RHT affecting Musculoskeletal System, Circulatory System, Nervous System, Energy level and digestive System, still more objective research needed to know the precise mechanism of action of RHT.
Some lacunae of this study caution interpretation within the context of its limitations. First the RHT reciepients volunteering to give feedback/ scores may be inclined towards beneficial effects by word of mouth by recommending friends family members. So inclination bias in self reported effects may not be ruled out. Second the sample size is restricted to participants taking intervention, and may not be representative of whole adult population in middle age, hence lacks generalisability until big sample size study is done. Since documentation / pilot data are required to begin further research, this study fulfills that perequisite. Further studies including wide variety of situations, disease conditions, and healthy controls for comparison in randomaised controlled trial manner will generate more evidences on intervention under our study.
Further studies required to study preventive aspects of RHT like other interventions also. Different population types, with various situations (morbid/ normal) with not only subjective but also objective paramaters required to assess inflammatory markers i.e. D-dimers, Serum Cortisol, C Reactive Protein, Natural killer (NK) cells, CD4 and CD8 counts, oxidative stress markers (Melondyaldehyde, Catalse etc) pre & post intervention to see differences. Some suggested tool may be used to assess effect of RHT like interventions more objectively are: blood flow velocity assessment using eco-ultrasound, lymphatic flow assessment using modern day techniques of scintigraphy, body flexibility- nerve muscle conduction velocity, Functional MRI, PET-CT may add value to research on such interventions.
The participants of this study were literate and digitally aware on how to respond to questions, a lesser literate partipant may respond in a different manner, when feedback is gathered using nondigital means-population (not technically literate) if included in future studies- the difference of opinions/ reposnse may become more visible and be very relevant for generalisability of such interventions. Using traditional pen paper/forms method to gather feedback using inperson interview may be different from verbatim expressed on digital medium. The changes/ effect of RHT may fade over a period of time. If any study is done using autoregressive paths of study design, it may allow researchers to isolate the effect of therapy on one or more variables/ parameters over the period of time and show difference from its own baseline status. This study provides valuable insights to do further research using two wave time legged design to measure more aspects of health at two different time points to examine their longitudinal relationship. A two wave cross legged panel design will help determining the direction of causality between variables over time and help to know more on how long effect of single session lasts, what are the benefits, if more sesstions are given and case specific requirements of sessions to get complete relief from symptoms. Since this is nonfunded study meticulous followup and objective parameters could not be done. Future work with proper research funds will sure reveal more on these aspects of RHT.
Japanese who live healthy lives as compared to world population has longevity too. Their low age standardized morbidity and mortality rates per one lakh population is majorly attributed to diet and life style habits and may be RHT type interventions practiced there. There is need to explore if RHT like interventions play role for prevention of disease and prolongation of life.
Our study enrolled middle income metro city adult population, who were mostly bothered by symptoms like pain, sleep, and mobility which affect quality of life, however there is need to include other interventions, various socioeconomical groups for comparison. Comparison needed with other available nonpharmocological noninvasive therapies like murma therapy, acupressure, meru chikitsa, Osteopathy, Carnioscaral therapy. Quantity and quality of effect of various other modalities, comparative assessment in various health situations, evaluation of outcomes not only in terms of visual analogue scale-VAS like this study, but also other validated tools markers (inflammatory biomarkers, and stress markers body fluid dynamics) will yield more usefull results. Randomized controlled trials will illuminate more potential biases too.
To understand /elaborate more on its mechanism and benefits, the randomized controlled trial with adjunct RHT intervention for patients in departments like Physical medicine rehabilitation, Physiotherapy, Endocrinology Medicine and Neurology may be enrolled to record subjective as well as objective markers. Some tests like eco–ultrasound to see changes in resistive index of blood through different veins and arteries may lit up mechanism of action on varicose veins, back pain, shoulder pain, fibroids, piles, polycystic ovarian syndrome body fluid related conditions.
Mechanical mauouvers of gentle strokes of RHT are supposed to triggers the release of endorphins, which are natural painkillers and mood elevators. These endorphins induced feelings of relaxation and well-being, unwind may also improve immunity hence, immune functionmay also be tested. It’s essential to remember that individual responses may vary hence RHT session’s need may vary in each condition, here in our study 3 to 5 sessions in 3 to 5 days (one session per day for 3 to 5 days) were given; however followup could have revealed need of more sessions and consistency/duration of effect.
Conditions affecting the lymphatic system, such as lymphedema can indirectly impact joint health and may exacerbate joint pain. Therefore, stimulated lymphatic function through Rakkehnho manuovers along with healthy diet, hydration can help promote joint health, regular bowl movement and alleviate pain. Removal of metabolic waste products from the brain may enhance cognitive function and mental clarity/Feeling mentally sharp/focused, and experiencing sense of wellbeing. This can manifest as feeling physically comfortable, emotionally balanced, and mentally alert as expressed by participants of the study in remarks. The lymphatic system is known for playing several roles in joint health, removes pathogens/ damaged cells, and foreign substances that could contribute to joint inflammation and pain and may have indirectly influenced joint health. The lymphatic vessels transporting excess fluid, cellular waste, and inflammatory molecules away from tissues may have helped reducing inflammation. Dysfunction in the lymphatic system impairs these processes, potentially exacerbating joint pain associated with inflammation. Adequate nutrient supply is crucial for maintaining joint health and supporting repair processes.
Since ours is nonfunded observational pilot data its most of the reporting is qualitative. Measuring effect by lymphatic flow in the body can be challenging because the lymphatic system is a complex network. Some research techniques directly measuring lymphatic flow are typically performed in laboratory settings and are not readily available for routine clinical use, . Like Lymphoscintigraphy (imaging technique involves injecting a radioactive tracer into the lymphatic vessels, which allows visualization of lymphatic flow using a gamma camera. Lymphoscintigraphy can provide more information about lymphatic drainage patterns and identify blockages or abnormalities in the lymphatic system, Near-Infrared fluorescence imaging utilizing fluorescent dyes that are injected into the lymphatic system, the dye emitting light in the near-infrared range, can be detected by specialized imaging systems. NIRF imaging can visualize lymphatic vessels and assess lymphatic flow in real-time during RHT. Lyphangiography -imaging technique of injecting a contrast agent into the lymphatic vessels followed by X-ray imaging- providing detailed images of the lymphatic system and identify abnormalities such as blockages or leaks can be tested pre and post RHT. Lyphedema is also measured measuring limb circumference to assess the extent of swelling. Bioimpedance analysis, lymphedema severity monitored over time using near-Infrared Fluorescence Imaging, functional imaging, dynamic contrast enhances MRI (magnetic resonance imaging) may also give insight in the lymphatic flow and tissue perfusion. However, these test methods are primarily used in research or in clinical settings and not available widely/ unsuitable for routine assessment during the therapy.
RHT manuovers must not be mistaken as regular type massage like Swedish massage, deep tissue massage, sports massage, Thai massage, and aromatherapy massage as it is quite different, it is also unlike other non pharmacological noninvasive techniques as mechanism is unique and different for its beneficial effects after sessions. It requires 45-60 minutes time and a calm, clean place with comfortable environment and two yoga mats.
Though, currently Rakkenho is performed as part of a holistic approach to health and wellness, its cost effectiveness needs comparison with other interventions. Its primarily focus is on promoting lymphatic flow but role in various musculo-skeletal, lymphatic system related morbidities, Lymphedema, Lymphadenopathy, Lymphangitis, Filariasis, Varicose veins etc needs documentation with collaboration of various healthcare professionals such as oncologist, hematologist, or physiotherapists, .
Conclusion: Rakkhenho (RHT) is a revival of lost wealth of holistic healing as observed herein for pain, sleep, joint movements. Its effectiveness is evident from this self reported feedback study. Further research on the mechanism of action and various other health conditions will further enhance knowledge on such usefull maneuvers.
Acknowledgement:
Gratefully acknowledging Ms. Jyoti Sanwal, Master Rakkenho therapist and Trainer at Sri Sri Wellbeing, Ms. Arunima Sinha, Faculty, VVKI, Dr. Sharika Menon, Sri Sri Panchkarma, and Ms. Chaya Khariya-Sri Sri Advanced Research Center for their valuable help in conducting the study and preparing manuscript.